...
Yelp Logo

CALL US NOW +1-844-669-0939

PRP for Orgasm Difficulty and Reduced Genital Sensation: What We Know

Written and medically reviewed by David Nazarian, MD — Board Certified in Internal Medicine and Medical Director of PRP Treatment Beverly Hills. Last medically reviewed: October 2026.

Quick answer: PRP is sometimes promoted for reduced genital sensation or difficulty reaching orgasm, but high-quality evidence is limited. Orgasmic difficulty can have hormonal, neurologic, medication-related, pelvic-floor, pain-related, and psychological causes, so evaluation should come before treatment.

Why orgasm difficulty occurs

  • Menopause or other hormonal changes
  • Antidepressants and other medications
  • Pelvic-floor dysfunction or pain
  • Neurologic conditions
  • Reduced arousal or lubrication
  • Relationship or psychological factors
  • Prior pelvic surgery or childbirth injury

What has been studied with PRP?

Small studies have included sexual-function questionnaires that measure desire, arousal, lubrication, orgasm, satisfaction, and pain. Some reported improvement after PRP, but study quality and protocols vary, and the evidence does not establish predictable benefit for orgasmic dysfunction.

What a consultation should address

The goal is to identify the dominant cause or causes, review medications and hormonal status when relevant, assess pain and pelvic-floor symptoms, and discuss established treatments. PRP can then be discussed honestly as an investigational option if appropriate.

See the main female sexual-function PRP page.

Important: PRP for sexual-function concerns is investigational/off-label. Evidence is limited and heterogeneous, and PRP should not be presented as a proven cure or replacement for established evaluation and treatment.

Medical references

PRP for Vaginal Dryness and Menopausal Sexual Symptoms: Evidence & Limitations

Written and medically reviewed by David Nazarian, MD — Board Certified in Internal Medicine and Medical Director of PRP Treatment Beverly Hills. Last medically reviewed: October 2026.

Quick answer: PRP has been explored for vaginal dryness and sexual symptoms, but evidence is preliminary. Vaginal dryness—especially around menopause—is commonly related to estrogen deficiency and genitourinary syndrome of menopause (GSM), and established treatments should be considered before or alongside experimental approaches.

Why vaginal dryness happens

Common contributors include menopause, breastfeeding, medications, autoimmune conditions, cancer therapies, pelvic-floor pain, and reduced arousal. A history and examination help distinguish these causes.

What is known about PRP?

Small studies of PRP in female sexual dysfunction have reported changes in vaginal-health and sexual-function scores, but protocols vary and high-quality evidence remains limited. PRP is not FDA-approved specifically for vaginal dryness or GSM.

Established options matter

Depending on the diagnosis, management may include vaginal moisturizers and lubricants, local hormonal therapy when appropriate, systemic menopause treatment in selected patients, pelvic-floor therapy, medication review, and treatment of pain or dermatologic conditions.

Where PRP may fit

For a carefully counseled patient who understands the uncertainty, PRP can be discussed as an investigational option—not as a replacement for diagnosis or established care.

See our PRP for female sexual dysfunction overview.

Important: PRP for sexual-function concerns is investigational/off-label. Evidence is limited and heterogeneous, and PRP should not be presented as a proven cure or replacement for established evaluation and treatment.

Medical references

PRP vs Shockwave Therapy for Erectile Dysfunction: Evidence & Differences

Written and medically reviewed by David Nazarian, MD — Board Certified in Internal Medicine and Medical Director of PRP Treatment Beverly Hills. Last medically reviewed: October 2026.

Quick answer: PRP injections and low-intensity shockwave therapy are different investigational or emerging approaches for ED. Shockwave therapy has been studied more extensively in vasculogenic ED, but protocols and long-term outcomes remain variable. PRP evidence is more limited.

How the approaches differ

Feature PRP Low-intensity shockwave
Method Autologous platelet concentrate injected into penile tissue External acoustic-energy treatment
Injections Yes No
Evidence base Limited and inconsistent Larger but still heterogeneous
Standardized protocol No No universal protocol
Established replacement for PDE5 inhibitors No No

Which has stronger evidence?

Low-intensity shockwave therapy has a broader clinical literature, particularly for vasculogenic ED, but results depend on device type, energy settings, patient selection, and protocol. PRP has fewer high-quality controlled studies. Neither should be marketed as a guaranteed regenerative cure.

Why diagnosis still comes first

Neither approach substitutes for evaluating cardiovascular disease, diabetes, testosterone status when appropriate, medication effects, neurologic causes, or psychological contributors. A patient with severe arterial disease or post-surgical neurovascular injury may have a very different prognosis from a patient with mild vasculogenic ED.

See our PRP for ED page for treatment details and current limitations.

Important: PRP for sexual-function concerns is investigational/off-label. Evidence is limited and heterogeneous, and PRP should not be presented as a proven cure or replacement for established evaluation and treatment.

Medical references

Why Erectile Dysfunction Should Be Evaluated—Not Just Treated With a Pill

Written and medically reviewed by David Nazarian, MD — Board Certified in Internal Medicine and Medical Director of PRP Treatment Beverly Hills. Last medically reviewed: October 2026.

Quick answer: Erectile dysfunction is a symptom, not a single diagnosis. Medication can be effective, but ED may also be an early clue to vascular disease, diabetes, medication effects, testosterone deficiency, sleep problems, neurologic disease, or psychological factors.

ED can be a vascular warning sign

Penile arteries are small, and vascular dysfunction can become clinically apparent as erectile difficulty. For some men, ED appears before overt cardiovascular symptoms. That does not mean every man with ED has heart disease, but it is one reason a medical history and risk assessment matter.

Common medical contributors

  • Hypertension and atherosclerotic risk
  • Diabetes and insulin resistance
  • Obesity and inactivity
  • Smoking
  • Medication adverse effects
  • Low testosterone when accompanied by compatible symptoms and confirmed testing
  • Sleep disorders
  • Neurologic disease
  • Pelvic surgery or radiation
  • Anxiety, depression, performance concerns, or relationship factors

Why a pill may work without answering the cause

Sildenafil and tadalafil improve erectile physiology for many men, but a response does not rule out an underlying health issue. Likewise, a poor response does not automatically mean a patient needs an injectable or regenerative procedure.

My approach

I start with the pattern of symptoms, medical history, medications, cardiovascular and metabolic risk, and laboratory testing when appropriate. Treatment can then be individualized. Standard options may include PDE5 inhibitors, risk-factor treatment, hormone treatment when true deficiency is present, vacuum devices, intracavernosal therapy, counseling, or urologic evaluation. PRP is a separate investigational discussion.

Related: PRP for erectile dysfunction and PRP vs Viagra/Cialis.

Medical references

PRP for Erectile Dysfunction: What Does the Scientific Evidence Show?

Written and medically reviewed by David Nazarian, MD — Board Certified in Internal Medicine and Medical Director of PRP Treatment Beverly Hills. Last medically reviewed: October 2026.

Quick answer: Clinical research on platelet-rich plasma for erectile dysfunction is promising enough to justify continued study, but not strong enough to establish PRP as routine standard-of-care therapy. Trials are small, preparation methods vary, and results have not been consistent.

Why PRP is being studied for ED

PRP contains platelets and signaling proteins involved in tissue repair biology. Researchers have investigated whether these signals might influence vascular or erectile tissue. A biologically plausible mechanism, however, is not the same as proven clinical effectiveness.

What randomized studies have found

Some randomized studies have reported improvements in erectile-function scores after intracavernosal PRP, while others have not shown a significant advantage over placebo. Differences in platelet concentration, injection technique, number of sessions, baseline ED severity, and follow-up make studies difficult to compare.

What major guidelines say

The American Urological Association has classified PRP for ED as experimental. European guidance has noted mild improvements in some studies but insufficient evidence for routine recommendation. This is why we do not describe PRP as a cure or as superior to established ED therapy.

What patients should take from the evidence

PRP may ultimately prove useful for a subset of men, but we do not yet know the optimal candidate, dose, preparation, number of sessions, or durability. Men considering it should understand the uncertainty and should still receive an evaluation for cardiovascular, metabolic, hormonal, medication-related, neurologic, and psychological contributors.

For practical comparisons, see PRP vs Viagra and Cialis and our main PRP for ED treatment page.

Important: PRP for sexual-function concerns is investigational/off-label. Evidence is limited and heterogeneous, and PRP should not be presented as a proven cure or replacement for established evaluation and treatment.

Medical references

Who Is a Good Candidate for PRP for Erectile Dysfunction?

Written and medically reviewed by David Nazarian, MD — Board Certified in Internal Medicine and Medical Director of PRP Treatment Beverly Hills. Last medically reviewed: October 2026.

Quick answer: There is no universally accepted evidence-based “ideal candidate” for PRP injections for erectile dysfunction because PRP remains investigational. Published studies have generally focused on men with mild to moderate organic or vasculogenic ED. The more important first step is determining why ED is occurring.

Why the cause of ED matters

Erectile dysfunction can be associated with vascular disease, diabetes, hypertension, medication effects, low testosterone, neurologic disease, pelvic surgery, sleep problems, smoking, obesity, psychological factors, and relationship factors. A treatment decision is stronger when it follows a diagnosis rather than simply a symptom.

Men who may be considered for a discussion about PRP

In research and clinical discussions, PRP is most often considered in men with mild to moderate erectile dysfunction who understand that the evidence is limited and who want to discuss investigational options alongside standard care. Men who have not been properly evaluated, have severe untreated cardiovascular risk, active infection, bleeding disorders, platelet disorders, or certain hematologic conditions may need additional evaluation or may not be appropriate candidates.

What if Viagra or Cialis is not working?

Failure of sildenafil or tadalafil does not automatically mean PRP is the next step. Dose, timing, sexual stimulation, medication interactions, vascular disease, diabetes, testosterone deficiency, neurologic disease, and post-prostate treatment changes should be reviewed first. Read our PRP vs Viagra and Cialis comparison.

What I evaluate before discussing PRP

  • Pattern and duration of ED
  • Cardiovascular and metabolic risk factors
  • Medication and supplement review
  • Testosterone testing when clinically appropriate
  • Prior response to PDE5 inhibitors
  • History of pelvic surgery or neurologic disease
  • Expectations and understanding of the investigational evidence

“The most important question is not whether someone can receive PRP. It is why the erectile dysfunction is occurring and whether we have addressed established causes and treatments first.” — David Nazarian, MD

Learn more on our main PRP for erectile dysfunction page.

Important: PRP for sexual-function concerns is investigational/off-label. Evidence is limited and heterogeneous, and PRP should not be presented as a proven cure or replacement for established evaluation and treatment.

Medical references

PRP vs Viagra and Cialis for Erectile Dysfunction: Evidence & Differences

Written and medically reviewed by David Nazarian, MD — Board Certified in Internal Medicine and Medical Director of PRP Treatment Beverly Hills.

Quick answer: Sildenafil (Viagra) and tadalafil (Cialis) are established PDE5-inhibitor treatments for erectile dysfunction and are recommended as first-line therapy for many men unless contraindicated. PRP injections for erectile dysfunction are being studied, but current evidence is not strong enough to consider PRP a replacement for PDE5 inhibitors. The best treatment depends on the cause of ED, cardiovascular health, medications, testosterone status, treatment goals, and response to standard therapy.

PRP vs Viagra and Cialis for Erectile Dysfunction

Men often ask whether PRP for erectile dysfunction can replace medications such as sildenafil or tadalafil. At this point, I would not frame the choice that way.

Viagra and Cialis work through a well-established pharmacologic pathway. They inhibit phosphodiesterase type 5 (PDE5), allowing cyclic GMP signaling to remain active longer in penile smooth muscle. In men with appropriate vascular and neurologic function, this can improve the ability to achieve and maintain an erection in response to sexual stimulation.

PRP is fundamentally different. It is prepared from the patient’s own blood and contains concentrated platelets and signaling proteins. Researchers are studying whether these platelet-derived signals may influence vascular or erectile-tissue biology. That is an interesting concept, but the clinical evidence remains limited.

“I do not see PRP as a substitute for Viagra or Cialis. I see it as an experimental biologic approach that still needs better evidence before we can say exactly who benefits, how much, and for how long.” — David Nazarian, MD

What Is the Best-Established First-Line Treatment?

For many men with erectile dysfunction, oral PDE5 inhibitors remain the best-established first-line medical therapy. Current European Association of Urology guidance recommends PDE5 inhibitors as first-line treatment for ED, and the American Urological Association recommends discussing FDA-approved PDE5 inhibitors such as sildenafil, tadalafil, vardenafil, and avanafil unless contraindicated.

That does not mean every patient should automatically receive a PDE5 inhibitor. ED can be a sign of cardiovascular disease, diabetes, medication effects, testosterone deficiency, neurologic disease, pelvic surgery, psychological factors, or other conditions. Evaluation matters.

Viagra vs Cialis: What Is the Difference?

Feature Sildenafil (Viagra) Tadalafil (Cialis) PRP
Type PDE5 inhibitor medication PDE5 inhibitor medication Autologous platelet-based injection
Evidence for ED Established Established Limited / investigational
Typical use As needed As needed or daily Injection protocol varies
Duration Shorter acting Longer acting; efficacy may extend up to 36 hours Long-term durability not established
FDA-approved for ED Yes Yes No
Important limitation Cannot be combined with nitrates Cannot be combined with nitrates Insufficient evidence for routine ED use

How Strong Is the Evidence for PRP in Erectile Dysfunction?

Several clinical studies have evaluated intracavernosal PRP in men with erectile dysfunction. Some trials have reported modest improvement in erectile-function scores, especially in men with mild to moderate organic or vasculogenic ED.

However, there are major limitations: small sample sizes, different PRP preparation methods, different injection protocols, short follow-up periods, and uncertainty about long-term durability. The European Association of Urology notes that PRP injections have produced mild improvement in some studies but that the available evidence remains insufficient to provide a recommendation for routine use. The AUA guideline has historically classified PRP therapy for ED as experimental.

For that reason, PRP should not be marketed as a proven cure for erectile dysfunction or as superior to established therapy.

Can PRP Help Men Who Do Not Respond to Viagra or Cialis?

That question is clinically more interesting than simply asking whether PRP is “better.” A man who does not respond to sildenafil or tadalafil may have several possible reasons for treatment failure:

  • Incorrect dose or timing
  • Insufficient sexual stimulation
  • Medication interactions
  • Severe vascular disease
  • Diabetes
  • Low testosterone
  • Neurologic disease
  • Post-prostate surgery changes
  • Psychological or relationship factors

Before moving to an experimental therapy, I would first make sure the diagnosis is correct and that established options have been used appropriately.

Can PRP Be Used Together With Viagra or Cialis?

There is no standard evidence-based protocol proving that combining PRP with sildenafil or tadalafil produces better outcomes than established therapy alone. Some clinicians may use combination strategies, but the benefit of PRP as an add-on remains uncertain.

Medication use around any procedure should be individualized. Patients should not start, stop, or combine erectile-dysfunction medications without discussing their medical history and current medications with their clinician.

What About Nitrates and Heart Disease?

Sildenafil and tadalafil can cause dangerous hypotension when combined with nitrate medications. Tadalafil is also contraindicated with guanylate cyclase stimulators such as riociguat. Men with significant cardiovascular disease should be evaluated before ED treatment because erectile dysfunction itself can sometimes be an early vascular warning sign.

PRP does not eliminate the need for cardiovascular evaluation. Treating the erection without evaluating the underlying cause can miss an important diagnosis.

Is PRP for ED FDA Approved?

No. PRP injections are not FDA-approved specifically for erectile dysfunction. Devices used to prepare PRP may have FDA clearance for blood-processing purposes, but that is different from FDA approval of PRP as an ED treatment.

Who Might Be Considered for PRP Research or Experimental Treatment?

Potential candidates discussed in published studies have often included men with mild to moderate organic or vasculogenic ED. However, there is no universally accepted PRP protocol or evidence-based patient-selection standard for routine clinical care.

If a patient is considering PRP, I think the discussion should include the strength of evidence, alternatives, expected uncertainty, cost, potential risks, and the fact that established ED therapies remain available.

My Approach to Erectile Dysfunction Treatment

I start with the cause of the erectile dysfunction. Depending on the patient, that evaluation may include cardiovascular risk factors, glucose control, blood pressure, medication review, testosterone testing when appropriate, sleep, weight, smoking, vascular health, and psychological contributors.

For many men, sildenafil or tadalafil is a reasonable first-line treatment. Others may need dose optimization, a different PDE5 inhibitor, vacuum therapy, intracavernosal medication, hormone treatment when true testosterone deficiency is present, or urologic evaluation.

PRP is different because it remains investigational. I would rather explain that uncertainty clearly than present it as a guaranteed regenerative solution.

Related erectile dysfunction guides

Frequently Asked Questions

Is PRP better than Viagra for erectile dysfunction?

Current evidence does not show that PRP is better than sildenafil. Sildenafil is an established, FDA-approved treatment for ED; PRP remains experimental.

Is PRP better than Cialis?

There is not enough evidence to conclude that PRP is better than tadalafil. Tadalafil is an established PDE5 inhibitor and can be used either as needed or in a daily regimen depending on the patient.

Does PRP permanently cure erectile dysfunction?

No reliable evidence shows that PRP permanently cures ED. Any claim of permanent restoration would go beyond current clinical evidence.

Can I take Viagra or Cialis after PRP?

Medication timing should be individualized by the treating physician. There is no universal evidence-based rule that applies to every PRP protocol or every patient.

Should I try PRP if Viagra or Cialis does not work?

Not automatically. First determine why the medication is not working. Dose, timing, cardiovascular disease, diabetes, testosterone deficiency, neurologic factors, and other causes should be evaluated before moving to an experimental therapy.

Medical References

Who Is a Good Candidate for PRP Hair Treatment? Early Hair Loss & Timing

Written and medically reviewed by David Nazarian, MD — Board Certified in Internal Medicine and Medical Director of PRP Treatment Beverly Hills.

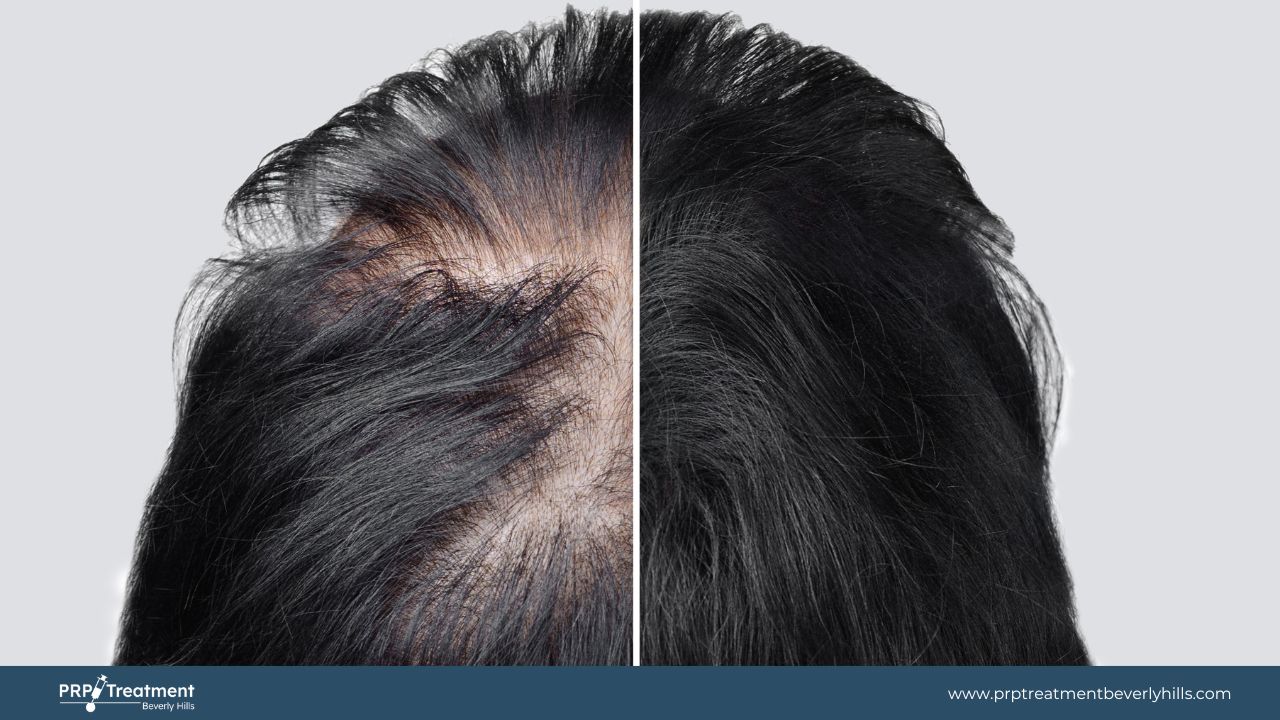
Quick answer: The best candidates for PRP hair treatment are usually patients with early to moderate, non-scarring hair loss who still have miniaturized but viable hair follicles. In my clinical experience, patients who come in while the hair is thinning—before an area becomes smooth and completely bald—tend to have the best opportunity to respond. PRP is not a guaranteed hair-regrowth treatment, and diagnosis matters because not every type of hair loss should be treated with PRP.

Who Is a Good Candidate for PRP Hair Treatment?

When I evaluate someone for PRP hair treatment, one of the first things I look at is how early the hair loss is and whether the follicles still appear to be present and miniaturized rather than absent.

“I often tell patients that a thinning follicle can be in limbo. It may not be functioning normally, but it may still be biologically active. Those are the patients I am most interested in treating early, before we lose that opportunity.” — David Nazarian, MD

That is an important distinction. PRP cannot reliably recreate a hair follicle that is no longer present. The goal is to support follicles that are still there but are becoming progressively smaller and producing thinner hairs.

Why Earlier Hair Loss Usually Gives Us a Better Opportunity

In androgenetic alopecia—male or female pattern hair loss—hair follicles gradually miniaturize. The hairs become finer, shorter, and less visible over time. Earlier in that process, there may still be a functioning follicular unit that can potentially respond to treatment.

This is why I usually prefer to treat patients before they have long-standing, smooth bald areas. The earlier we identify the pattern and begin an appropriate treatment plan, the more options we usually have.

PRP has been studied most extensively for androgenetic alopecia. Systematic reviews have found that PRP may improve hair density and other hair-growth measures in selected patients, although study protocols vary and the overall quality of evidence is not uniform. That variability is important: PRP should be presented as a treatment option, not a guaranteed cure.

How PRP May Help Miniaturized Hair Follicles

PRP is prepared from the patient’s own blood and contains a concentrated platelet fraction. Platelets release signaling molecules including growth factors and cytokines that are involved in tissue repair, vascular signaling, and cell-to-cell communication.

Researchers have proposed several mechanisms that may be relevant to hair follicles, including:

  • Angiogenic signaling: PRP contains mediators such as VEGF and other growth factors that may support formation of new microvasculature and improve the local follicular environment.
  • Follicular signaling: PRP has been associated with signaling pathways involved in cell survival, proliferation, and the hair-growth cycle, including Wnt/β-catenin, Akt/ERK, and related pathways.
  • Support of the anagen phase: PRP may encourage susceptible follicles to enter or remain in the active growth phase longer.
  • Controlled microtrauma from injection: The injections themselves create small, intentional tissue injuries. Microtrauma can initiate a local wound-healing response, increase growth-factor signaling, and may contribute to increased local blood flow and vascular response.

I explain this to patients in practical terms: we are trying to improve the environment around a follicle that is struggling, not manufacture a brand-new follicle where none remains.

Does PRP “Revive” Hair Follicles?

I use the word “revive” conversationally with patients because it is an easy way to explain the concept, but medically the process is more nuanced. A follicle affected by androgenetic alopecia may become progressively miniaturized and produce thinner hair fibers while remaining biologically active.

PRP may support that follicle through growth-factor signaling, angiogenesis, and changes in the local tissue environment. However, if an area has been completely bald for many years and there are few recoverable follicular units remaining, PRP is much less likely to produce meaningful regrowth.

Who Tends to Be the Best PRP Hair Candidate?

The patients I am most interested in evaluating for PRP are those with:

  • Early or moderate androgenetic alopecia
  • Progressive thinning rather than completely smooth bald areas
  • Visible miniaturized hairs in the affected region
  • Recent widening of the part or thinning of the crown
  • Early recession with remaining follicular activity
  • A realistic understanding that PRP may improve density or thickness but does not guarantee full restoration

Men and women can both be candidates. The treatment plan may differ depending on the pattern of hair loss, age, hormonal factors, pregnancy potential, medications, and whether medical therapy such as minoxidil or finasteride is also appropriate.

Who May Not Be a Good Candidate?

PRP should not be used as a reflex treatment for every person who reports hair loss. Patients may be poor candidates when the underlying problem is not androgenetic alopecia or when there is advanced loss with limited remaining follicular activity.

Examples include:

  • Scarring alopecia: inflammatory scarring disorders can permanently destroy follicles and often require dermatologic evaluation and anti-inflammatory treatment.
  • Active infection: fungal or bacterial scalp disease should be diagnosed and treated first.
  • Uncorrected medical or nutritional causes: thyroid disease, iron deficiency, severe nutritional deficiency, medication effects, and systemic illness may need to be addressed.
  • Alopecia areata: autoimmune patchy hair loss has a different treatment pathway; intralesional corticosteroid therapy such as Kenalog may be appropriate in selected cases.
  • Long-standing smooth bald areas: if functional follicles are no longer present, PRP cannot be expected to recreate them.

For a broader explanation of these diagnoses, see our guide to alopecia causes and treatment.

Why Diagnosis Comes Before PRP

This is one of the most important points I want patients to understand: hair loss is a symptom, not a diagnosis.

Before recommending PRP, I want to know why the patient is losing hair. The pattern, rate of progression, scalp appearance, family history, medications, nutrition, recent illness, hormone history, and other medical factors all matter.

In some patients, evaluation may include dermoscopy, selected laboratory testing, fungal testing, or referral for scalp biopsy. A person with androgenetic alopecia should not be treated the same way as someone with alopecia areata, telogen effluvium, traction alopecia, or cicatricial alopecia.

PRP, Minoxidil, and Finasteride: Sometimes the Best Plan Is Combination Treatment

PRP does not necessarily replace established medical therapy. In appropriate patients, I may discuss combining PRP with treatments such as minoxidil or finasteride because they work through different mechanisms.

Minoxidil can support the hair-growth cycle, while finasteride reduces DHT-driven follicular miniaturization in appropriate male patients. PRP may provide an additional biologic stimulus. The best combination depends on the diagnosis and the individual patient.

For more detail, see our guide to finasteride, minoxidil, and PRP for hair loss and our article on how Rogaine/minoxidil works.

What About PRF for Hair Loss?

PRF hair treatment is another autologous blood-derived approach. It differs from PRP in preparation and in the fibrin matrix it contains. PRF is being studied for androgenetic alopecia, but the evidence base and treatment protocols remain less standardized.

I do not think the right question is simply “PRP or PRF—which is better?” The more important question is whether the patient has a type and stage of hair loss that is likely to benefit from a platelet-based treatment at all.

How Soon Should You Treat Hair Loss?

If you notice progressive thinning, widening of the part, reduced density at the crown, or early recession, I would rather evaluate it sooner than later. That does not mean everyone needs PRP immediately. It means we should identify the cause while more treatment options may still be available.

“With hair loss, time matters. I would rather see a patient when the follicles are miniaturizing than after an area has been completely bald for years.” — David Nazarian, MD

What Results Should You Expect?

PRP results vary. Some patients may see improvement in shedding, hair caliber, or density over several months, while others may have little visible response. Multiple sessions are commonly used in published protocols, but there is no single universally accepted regimen.

We track progress with standardized photographs and reassess whether the treatment is producing a meaningful benefit. See our guide to PRP hair before-and-after results and timeline.

My Approach to PRP Hair Restoration in Beverly Hills

My approach is simple: diagnose first, treat early when appropriate, and avoid promising that PRP can restore hair in every patient.

The best candidate is usually not the person with the most advanced hair loss. It is often the person who notices that the hair is starting to thin and still has miniaturized follicles that may be capable of responding.

If you are considering PRP hair restoration in Beverly Hills or Los Angeles, the first step is an evaluation to determine the cause and stage of the hair loss and whether PRP, PRF, medical therapy, or another approach makes the most sense.

Frequently Asked Questions

Is PRP better for early hair loss?

Generally, PRP is more biologically plausible when miniaturized but viable follicles remain. Long-standing smooth bald areas are less likely to respond because PRP cannot reliably create new follicles where functional follicular units are absent.

Can PRP bring back dead hair follicles?

PRP should not be described as reliably bringing dead follicles back to life. It may support miniaturized or struggling follicles that are still biologically active, but it cannot be expected to recreate a completely absent follicle.

Does PRP increase blood flow to hair follicles?

PRP contains angiogenic signaling molecules, including VEGF, and proposed mechanisms include angiogenesis and vascular support around hair follicles. Injection-related microtrauma may also contribute to a local wound-healing response and circulation changes.

What type of hair loss responds best to PRP?

The strongest clinical evidence is for androgenetic alopecia, also called male or female pattern hair loss. Other types of hair loss require diagnosis-specific treatment.

Is PRP FDA-approved for hair loss?

No. PRP is not FDA-approved specifically as a treatment for androgenetic alopecia. Preparation methods and treatment protocols vary, which is one reason results differ across studies.

Medical References

PRP Under Eyes: Which Dark Circles Can It Help—and Which Can’t It?

By David Nazarian, MD — Board Certified in Internal Medicine

A lot of patients come to me because they are concerned about dark circles, hollowing, or bags underneath their eyes. One of the most important things I explain is that these problems can look similar, but they do not necessarily have the same cause—and that matters when deciding whether PRP or PRF is likely to help.

Before recommending injections, I first try to determine why the under-eye area looks dark or hollow.

Dark circles are not one diagnosis

Dark circles can be caused by several different factors. In some patients, allergies or chronic nasal congestion may contribute to discoloration, irritation, or frequent rubbing around the eyes. In those situations, treating the allergy component can be an important part of the plan.

Other patients have true pigment in the skin. Others have volume loss that creates a shadow in the tear-trough area. Some have thin or crepey skin, while others have prominent fat pads that create true under-eye bags.

Those are different problems, and I do not expect one procedure to treat all of them equally well.

When allergies may be contributing

If a patient has symptoms such as nasal congestion, sneezing, itching, watery eyes, or frequent eye rubbing, I consider whether allergies may be contributing to the appearance of the lower eyelids. When medically appropriate, I may first address those symptoms with treatments such as antihistamines or nasal sprays.

In those patients, I do not want to treat only the appearance while ignoring a potentially correctable cause.

When hollowing creates the appearance of darkness

Sometimes the skin itself is not especially dark. Instead, volume loss under the eye creates a depression and shadow, making the area look darker.

That distinction is important because a treatment aimed at skin quality is different from a treatment aimed at restoring significant volume. PRP or PRF may be considered in selected patients with mild hollowing or skin-quality concerns, but I do not present them as a substitute for every volume-restoration treatment.

What about true under-eye bags?

Prominent lower-eyelid fat pads can create true bags beneath the eyes. PRP or PRF does not remove those fat pads. If fat prolapse is the dominant problem, another treatment may be more appropriate.

This is one reason an in-person examination matters. A patient may describe the problem as “dark circles,” while the main issue is actually structural.

Where PRP and PRF may fit

PRP and PRF contain platelets and signaling proteins that are being studied for their effects on tissue quality, collagen remodeling, and local cellular signaling. In appropriately selected patients, some improvement may be seen in skin texture, mild hollowing, or the appearance of dark circles.

PRF also contains a fibrin matrix that releases platelet-derived signaling factors over time. In selected patients, I may favor PRF when the goal is to support tissue quality or provide subtle fullness.

Results vary, and neither treatment should be presented as a guaranteed way to eliminate dark circles.

Why I often recommend two to three sessions

For many patients, I begin with approximately two to three treatments spaced about one month apart. The goal is to provide a series of treatments while tissue remodeling takes place gradually.

I then allow time for the under-eye area to respond before deciding whether more treatment is appropriate.

When pigmentation is part of the problem

In some patients, the darkness is caused partly by true skin pigmentation. In those cases, injections alone may not be enough.

Depending on the patient’s skin type and examination, I may discuss topical treatments such as vitamin C, hydroquinone, or other pigment-modulating agents when medically appropriate. These treatments need to be used carefully around the eyes because irritation can sometimes worsen pigmentation.

My clinical approach

When a patient asks me whether PRP or PRF can treat dark circles, I usually work through several questions first:

  • Is there allergy-related discoloration or frequent eye rubbing?
  • Is there true pigment in the skin?
  • Is hollowing or volume loss creating a shadow?
  • Is there thinning or crepey skin?
  • Are prominent fat pads creating true under-eye bags?
  • Would PRP or PRF realistically address the patient’s main concern?

For me, the key is not simply choosing an injection. It is diagnosing the reason for the under-eye appearance and matching the treatment to that cause.

For more information about candidacy, recovery, pricing, and treatment options, visit our PRP Under-Eye Treatment in Beverly Hills & Los Angeles page.

Individual results vary. This article is educational and does not replace an individualized medical evaluation.

Who Actually Responds Best to PRP for Hair Loss? My Clinical Approach

By David Nazarian, MD — Board Certified in Internal Medicine

For the clinical treatment overview, candidacy, process, risks and pricing, see our PRP Hair Loss Treatment & Hair Restoration in Los Angeles & Beverly Hills service page.

A large number of men come to my office concerned about thinning hair or progressive hair loss. I have used platelet-rich plasma, or PRP, as one treatment option for appropriately selected patients, but one of the most important things I explain is that PRP is not equally effective for everyone.

The first question I ask is not simply whether someone wants PRP. It is: why is this patient losing hair?

Before PRP, I want to understand the cause of the hair loss

Hair loss is not always simply genetic male-pattern hair loss. In some patients, there may be other factors contributing to shedding or thinning that they are not aware of. Depending on the history and examination, I may evaluate for issues such as iron or other nutrient deficiencies, vitamin deficiencies, thyroid or hormonal abnormalities, medications, significant stress, poor sleep, recent illness, weight changes, or other medical conditions.

When appropriate, I use blood testing to look for potentially correctable contributors. My goal is not simply to inject the scalp while ignoring a problem that may be contributing to the hair loss in the first place.

Who tends to respond better to PRP?

In my experience, PRP tends to make the most sense in patients who still have viable, miniaturizing hair follicles rather than areas where follicles have been absent for a long period of time.

This distinction matters. PRP should not be presented as a way to recreate hair follicles that are no longer viable. Once an area has advanced to longstanding complete follicular loss, the likelihood of meaningful regrowth from PRP alone is substantially lower.

This is one reason I generally prefer to intervene earlier in the hair-loss process rather than waiting until the scalp has been bald for many years.

What is PRP trying to do?

PRP contains platelets and a mixture of signaling proteins and growth factors. Laboratory and clinical research suggests that these factors may influence cellular signaling around the hair follicle and may support the activity of follicles that are still present.

Scalp injections also create a local tissue response, and researchers have studied whether PRP may influence vascular signaling and blood supply around the follicle. These biological mechanisms are still being investigated, and they should not be interpreted to mean that PRP can reliably regenerate a dead hair follicle.

What matters clinically is whether a patient still has follicles capable of responding.

Hair growth takes time

One of the most common misconceptions I hear is, “When am I going to see the new hair?” Some patients expect a visible change within several weeks. Hair biology simply does not move that quickly.

Hair follicles cycle through different phases, and changes in density, thickness, or shedding generally need to be evaluated over months—not days or weeks.

I usually tell patients that early changes may take several months to appreciate, while a more meaningful assessment of response often occurs around 6 to 12 months.

That is also why I encourage patients not to judge the treatment after one month.

Why I often begin with three treatments

For many patients, my initial protocol is a series of approximately three PRP treatments spaced about one month apart, although the schedule can vary depending on the patient’s diagnosis and clinical situation.

The rationale is to provide a concentrated initial treatment period while the follicles are being exposed to repeated platelet-derived signaling factors.

After that initial series, I generally give the hair time to respond. Some patients later choose maintenance treatment at approximately six months or one year, but I do not believe that every patient should automatically be placed on the same maintenance schedule. I look at the patient’s response, pattern of hair loss, other treatments being used, and overall goals.

My overall approach

For me, PRP hair restoration is not simply an injection procedure.

  • Why is this patient losing hair?
  • Are there correctable medical or nutritional factors?
  • Are the follicles still viable?
  • Is this the type of hair loss that is reasonably likely to respond?
  • Are we setting realistic expectations?
  • Should PRP be used alone or alongside another evidence-based hair-loss treatment?

The patients who tend to be happiest are the ones who understand from the beginning that hair restoration is a process and that PRP is one tool within a broader treatment strategy—not a guaranteed or immediate cure.

For more information about evaluation, candidacy, treatment planning, pricing and what to expect, visit our PRP Hair Treatment & Restoration in Beverly Hills & Los Angeles page.

Individual results vary. This article is educational and does not replace an individualized medical evaluation.